
 EN

-

Redefining diuretics use in hypertension: why select a thiazide-like diuretic ?
Redefining diuretics use in hypertension: why select a thiazide-like diuretic ? Michel Burnier, George Bakris, and Bryan Williams
-
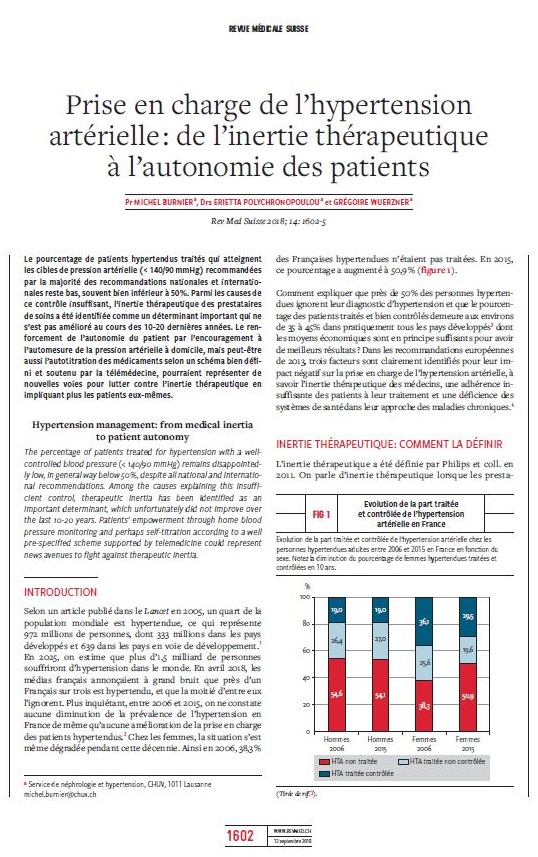
Prise en charge de l’hypertension artérielle : de l’inertie thérapeutique à l’autonomie des patients
Pr MICHEL BURNIER, Drs ERIETTA POLYCHRONOPOULOU et GRÉGOIRE WUERZNER
-

Nouvelles cibles tensionnelles : beaucoup de bruit pour rien ?
Comment accepter la réduction des cibles tensionnelles au quotidien lorsque plus de la moitié des patients hypertendus traités ont des valeurs de pression au-dessus des « anciennes » cibles ? La publication de nouvelles recommandations relatives au diagnostic de l’hypertension et aux cibles de pression artérielle à atteindre nous replonge régulièrement dans un questionnement quasi lelouchien : Tout ça pour ça ?
-

Optimizing hypertension management in renal transplantation: a call to action
Cardiovascular events represent a major cause of death in renal transplant patients [1,2]. Renal transplant recipients also constitute a population at very high risk for progressive graft loss and renal events. Although immunological risk factors play an important role in renal survival, it is less recognized that hypertension is probably the major nonimmunological risk factor for graft loss [2]. Accurate diagnosis of hypertension and adequate control of blood pressure (BP) is considered as a fundamental goal in the management of renal transplant patients to lower their cardiovascular and renal risk. However, diagnosis, treatment and monitoring of hypertension remain suboptimal in most renal transplant patients [3]. This editorial is a call for action aiming at improving hypertension control in the transplant population.
Articles récents
- Poor Physician Adherence to Clinical Guidelines in Hypertension—Time for Physicians to Face Clinical Inertia

- Dietary sodium intake does not alter renal potassium handlingand blood pressure in healthy young males

- Management of hypertensive disorders inpregnancy: a Position Statement of the EuropeanSociety of Hypertension Working Group‘Hypertension in Women’

- Gout and hyperuricaemia: modifiable cardiovascular risk factors?

- Women’s health, cardiovascular risk and hypertension: the perspective still needs to improve
